Muscular Dystrophy On Flowvella
Clinical characteristics. Congenital muscular dystrophy (CMD) is a clinically and genetically heterogeneous group of inherited muscle disorders.
Muscle weakness typically presents from birth to early infancy. Affected infants typically appear 'floppy' with low muscle tone and poor spontaneous movements. Affected children may present with delay or arrest of gross motor development together with joint and/or spinal rigidity.
Muscle weakness may improve, worsen, or stabilize in the short term; however, with time progressive weakness and joint contractures, spinal deformities, and respiratory compromise may affect quality of life and life span. The main CMD subtypes, grouped by involved protein function and in which causative allelic variants occur, are laminin alpha-2 (merosin) deficiency (MDC1A), collagen VI-deficient CMD, the dystroglycanopathies (caused by mutation of POMT1, POMT2, FKTN, FKRP, LARGE1, POMGNT1, and ISPD), SELENON ( SEPN1)-related CMD (previously known as rigid spine syndrome, RSMD1) and LMNA-related CMD (L-CMD). Several less known CMD subtypes have been reported in a limited number of individuals. Cognitive impairment ranging from intellectual disability to mild cognitive delay, structural brain and/or eye abnormalities, and seizures are found almost exclusively in the dystroglycanopathies while white matter abnormalities without major cognitive involvement tend to be seen in the laminin alpha-2-deficient subtype.
Genetic counseling. The muscular dystrophies are inherited in an manner with the following exceptions: collagen VI-deficient CMD, which may be inherited in an autosomal recessive or an manner; LMNA-related CMD (L-CMD), which is inherited in an autosomal dominant manner with all cases to date caused by a.
In subtypes, each sib of an individual has a 25% chance of being affected, a 50% chance of being an asymptomatic, and a 25% chance of being unaffected and not a carrier. Carriers are asymptomatic.
Carrier testing for at-risk relatives and prenatal testing for pregnancies at increased risk are possible if the pathogenic variants in the family are known. In subtypes, the offspring of individuals have a 50% chance of being affected. The risk to sibs of an individual with an apparent is low, but not zero because of the possibility of in one of the parents. Prenatal testing for pregnancies at increased risk is possible for families in which the pathogenic variant has been identified. Treatment of manifestations: Treatment tailored to an individual’s needs is best managed by a multidisciplinary team.
Speech therapy and swallowing studies are used to evaluate those with feeding difficulties and/or possible aspiration. Interventions may be needed for inadequate weight gain and poor feeding. Aspiration pneumonia and/or respiratory insufficiency may require assisted cough devices, supplemental oxygen, noninvasive ventilation, and/or mechanical ventilation via tracheostomy.
Physical therapy focuses on stretching exercises of the spine and limbs and to prevent contractures, and positive pressure devices or ventilation to promote mobility of the thoracic cage. Splints, braces and surgical intervention are used to prevent and treat spinal and limb contractures and deformities; these and other assistive devices may help posture, ambulation, and mobility. Epilepsy, behavior problems, and/or intellectual disability require specific treatment and interventions. Vaccinations, early treatment of pulmonary infections, and attention to oral hygiene and care are important aspects of routine care. With support for their physical disabilities the vast majority of children with CMD who have normal cognitive development benefit socially and educationally from mainstreaming into regular educational facilities.
The multidisciplinary team can provide social and emotional support for patients and caregivers. Surveillance: Routine monitoring of feeding and weight gain, respiratory function, strength, and mobility; annual or biannual monitoring for orthopedic and pulmonary complications; cardiac monitoring for those with CMD subtypes involving a risk for cardiomyopathy. Those with CMD subtypes with central nervous system involvement require surveillance for possible seizures and/or behavioral problems. Definition of CMD The term muscular dystrophy (CMD) refers to a heterogeneous group of inherited disorders in which weakness is first apparent at birth or in infancy. With the discovery of causative pathogenic variants in multiple genes in the last two decades, the concept of CMD has evolved from a narrowly defined clinical diagnosis (onset in the first months of life) and histologic diagnosis (dystrophic muscle on biopsy) to a more inclusive group of subtypes defined by genes in which causative pathogenic variants occur. No complete or satisfactory classification system exists; furthermore, phenotypes overlap both within CMD subtypes and among the congenital muscular dystrophies, congenital myopathies, and limb-girdle muscular dystrophies (see ).
Nonetheless, the umbrella term CMD remains useful by providing a framework for the diagnostic approach to the infant or young child with muscle weakness. Clinical Manifestations of CMD Hypotonia and muscle weakness are present at birth or during infancy. Poor or decreased motor abilities, delay or arrest of motor milestones, and joint or spinal deformities are often the presenting features of CMD. The age of onset is usually not clearly defined and often difficult to identify retrospectively. Since delay of motor skill acquisition may be a presenting symptom of CMD, onset of manifestations before age two years may be a reasonable diagnostic criterion. Although muscle weakness of CMD may be stable in the short term, typically over time the weakness and its complications become more severe. These complications include feeding difficulties leading to poor nutrition; respiratory insufficiency; joint contractures and scoliosis; and, in some subtypes, cardiac involvement.
The central nervous system, eye, and connective tissue may also be involved. Note: The diagnosis of a child who has delay in onset of walking during the first two years of life as having CMD versus limb-girdle muscular dystrophy (LGMD) may be considered a matter of convention especially given the overlap between the CMD and LGMD phenotypes (see ). Note that the presence or absence of intellectual impairment does not distinguish CMD from LGMD; it is strictly the age of onset of muscle weakness in late childhood or adulthood that defines LGMD. Subtypes of CMD of Known Cause Click for background information (pdf).
The classification scheme for subtypes of CMD that is used in this GeneReview is based on the in which pathogenic variants occur and organized by the cellular localization of the protein encoded by the gene: structural proteins of the extracellular matrix, defects in glycosylation, proteins of the endoplasmic reticulum, and proteins of the nuclear envelope (see ). Although phenotypic classification has also been proposed, such a classification has its shortcoming because the phenotypes caused by pathogenic variants in different genes can overlap significantly and pathogenic variants in one gene can be associated with a spectrum of clinical phenotypes. The disorders associated with mutation of the 13 genes most commonly associated with CMD are summarized in ,. Description of several less known CMD subtypes, reported in a limited number of individuals, follows.
To date, data for all CMD subtypes are insufficient to make any firm / correlations or to provide definitive prognosis or anticipatory guidance based on CMD subtype. Of note, in large cohorts of individuals with CMD causative pathogenic variants can be identified in 25%-50% of cases, underscoring the need for ongoing investigation into the genetic causes of CMD and the need to consider disorders included in the in the evaluation of an individual with possible CMD. Clinical Findings in the Disorders Described in Laminin alpha-2 deficiency ( LAMA2-related CMD MDC1A) is characterized by hypotonia, delayed or arrested motor milestones, and feeding difficulties.
Muscle weakness is absent or slowly progressive. Respiratory insufficiency and orthopedic complications may become severe, with diffuse joint contractures and spinal rigidity. Progressive restrictive respiratory insufficiency occurs in all non-ambulatory persons. Nocturnal mechanical ventilation or continuous ventilation via tracheostomy may be required either early on or beyond age ten to 15 years. Most children with laminin alpha-2 deficiency who have complete deficiency of the protein merosin do not acquire independent walking, but ambulation in those with partial merosin deficiency with later onset has been reported.
With time children develop typical myopathic facies and some develop external ophthalmoplegia and may appear to have an enlarged head with parents relaying difficulty in pulling T-shirts over the head. Of note, retrospective data on 15 children with laminin alpha-2 deficiency from one CMD center revealed that 53% had a head circumference above the 90 th centile Author, personal observation. Cognitive abilities are normal in the majority of individuals. Seizures are observed in 20%-30%. Brain MRI demonstrates diffuse white matter signal abnormalities sparing the cerebellum, corpus callosum, and internal capsule. Children may initially be misdiagnosed as having a leukodystrophy.
The MRI findings can be found consistently beyond age six months. White matter changes do not regress with time. A small number of individuals have structural changes with focal cortical dysplasia that tends to involve the occipital and temporal lobes. Nerve conduction studies show reduced velocities during disease demonstrating a peripheral neuropathy. Inheritance is. The collagen VI-deficient CMDs were previously known as Ullrich muscular dystrophy (UCMD) and Bethlem myopathy (see ). Although originally described as separate entities, UCMD and Bethlem myopathy represent a clinical continuum; intermediate phenotypes are common.

In a recent study of 49 individuals with collagen VI myopathy, referred to three phenotypes:. UCMD (first described as 'scleroatonic myopathy') is characterized by weakness and hypotonia along with congenital joint or spinal rigidity or deformities. The combination of proximal joint contractures and a striking hyperlaxity of the distal joints is characteristic. Some children have acquired the ability to walk independently; however, disease progression often results in loss of ambulation. Early and severe respiratory involvement may require ventilatory support in the first or second decade of life.
Bethlem myopathy is characterized by the combination of proximal muscle weakness and variable contractures, affecting most frequently the long finger flexors, elbows, and ankles. Although the first reports of UCMD showed transmission, most individuals identified in recent years have a.
Bethlem myopathy is typically caused by autosomal dominant pathogenic variants, but a few instances of autosomal recessive transmission have been reported. Dystroglycanopathies are characterized by a broad CMD phenotypic spectrum with and without intellectual disability, eye involvement, and brain findings. Several CMD phenotypes known to be dystroglycanopathies were initially described as syndromes (in descending order of severity):. MDC1C Eye manifestations can include either unilateral or bilateral microcornea and/or microphthalmia, hypoplastic or absent optic nerves, and colobomas that may involve the retina.
Anterior chamber malformations include cataracts, iris hypoplasia or malformation, and abnormal or shallow anterior chamber angle which can result in glaucoma. Retinal dysplasia or detachment may occur. In individuals with milder manifestations of a dystroglycanopathy, high myopia or optic disc pallor may be the only ocular manifestation. Brain MRI may demonstrate structural abnormalities (e.g., hydrocephalus, brain stem hypoplasia, cerebellar cysts) or abnormalities in neuronal migration (cobblestone lissencephaly or polymicrogyria), which are common. White matter changes may regress with time. Hindbrain malformations can include atrophy of the cerebellar vermis and hemispheres and flattening of the pons and brain stem. Other findings can include partial absence of the corpus callosum, hypoplasia of the pyramidal tracts, and obstructive hydrocephalus requiring a shunt.
WWS, MEB disease, and FCMD were considered separate entities long before their molecular basis was known. When clinically defined, these three disorders did not include milder phenotypes in which the brain MRI was normal or showed less severe cortical or cerebellar malformations. The spectrum of the dystroglycanopathies is now known to include the milder of limb-girdle muscle muscular dystrophy, with and without cognitive impairment. Pathogenic variants in a number of genes ( ISPD, POMT1, POMT2, POMGNT1, FKTN, FKRP, and LARGE1) lead to alpha dystroglycan-related muscular dystrophy.
The proteins encoded by these genes (which are involved in critical steps in both O-mannosylation and the elaboration of glycan chains on alpha dystroglycan) include:. Proteins involved in a specific glycan epitope that confers laminin binding (encoded by FKTN, FKRP, and LARGE1). Although 'one, one syndrome' was initially postulated, it is now known that pathogenic variants in any one of the seven genes results in a broad phenotypic spectrum. The most phenotypic variability is observed with pathogenic variants in FKTN and FKRP, which result in phenotypes ranging from WWS to CMD, LGMD, elevated creatine kinase (CK), and exercise intolerance without intellectual disability and normal brain MRI.
Homozygous and ISPD pathogenic variants are associated with a severe dystroglycanopathy subtype of CMD with brain and eye involvement (Walker-Warburg ). Certain clinical findings can help direct one to the specific involved:. Microphthalmia, retinal detachment, retinal hypoplasia, anterior chamber malformation, cataracts SELENON ( SEPN1)-related CMD. SELENON pathogenic variants were initially described in CMD characterized by selective spinal rigidity and normal expression of the protein merosin (rigid spine muscular dystrophy type 1 RSMD1). It is now known that 'rigid spine syndrome' is not specific to this subtype of CMD and that some spinal rigidity resulting from paraspinal contractures may develop in other CMD subtypes. Clinical features tend to be homogeneous: cervicoaxial weakness early in life that may be associated with delay in motor milestones and development of spinal stiffness often associated with thoracic spinal lordosis and a characteristic 'S'-shaped thoracic scoliosis. Progressive respiratory insufficiency is aggravated by diaphragmatic weakness.
Early nocturnal hypoventilation prior to adulthood in a person who is still ambulatory is the distinct feature of this CMD subtype. MRI shows selective involvement of the sartorius and major adductor muscles in the thigh giving a characteristic medial thigh wasting, notable on physical examination. SELENON pathogenic variants are also reported in the classic form of, in, and in a desminopathy with Mallory body-like inclusions. LMNA-related CMD (L-CMD) is part of the spectrum of laminopathies (also known as nuclear envelopathies).
L-CMD may present with a severe picture in the first six months of life (absence of head or trunk support) or with progressive loss of head support after acquisition of sitting or walking ability (dropped head syndrome). Often hypotonia and weakness of the axial-cervical muscles is rapidly progressive, followed by more slowly progressive weakness the proximal upper limbs and distal lower limbs. Facial muscles are spared. With time, the characteristic findings are head lag, thoracic and lumbar spinal hyperextension (rigidity), lower limb contractures, and talipes equinovarus but no significant upper limb contractures. Restrictive lung disease resulting in respiratory insufficiency occurs as muscle weakness progresses. Mechanical ventilation may be required before age two years in those more severely.
L-CMD can be considered as an early-onset variant of (EDMD), without some of the typical early findings of EDMD (elbow contractures and major cardiac complications). Nonetheless, these findings may develop in time. Genetic testing has identified a number of dominant pathogenic variants which have not been found in persons with milder phenotypes of EDMD. Moreover, among the small number of individuals identified to date, several share the same suggesting a possible - correlation. Less Common CMD Subtypes Integrin α7 deficient CMD. This subtype has only been described in three individuals worldwide.
Phenotype is variable. Integrin alpha 9 deficient CMD. Recently, a caused by deficiency in integrin alpha 9 that overlaps with collagen VI-deficient CMD was described in the French-Canadian population in Quebec. Distal hyperlaxity is localized to metacarpal phalanges rather than fingers. Scoliosis of severity may be observed during disease course. SYNE1-related CMD.
CMD with adducted thumbs, intellectual disability, cerebellar hypoplasia, and cataracts caused by a in SYNE1, encoding enaptin (nesprin-1), a nuclear envelope protein. CHKB-related muscle disease (megaconial type CMD).
Homozygous and CHKB pathogenic variants were recently identified in individuals with early-onset muscle wasting, severe intellectual disability, and mitochondrial structural abnormalities in muscle (enlargement of mitochondrial at fiber periphery, depletion of mitochondria at fiber center). Dilated cardiomyopathy and other cardiac anomalies were identified in some individuals. Establishing the Diagnosis of a CMD Subtype Establishing the specific CMD subtype can help clarify prognosis and inheritance pattern. Establishing the subtype usually involves medical history, family history, physical examination, neurologic examination, eye examination by a pediatric ophthalmologist, measurement of serum CK concentration, neuroimaging, muscle imaging, muscle and/or skin biopsy for histologic examination and immunohistochemistry,. Medical history. In infants medical history focuses on fetal movement, perinatal history and birth size, acquisition of motor milestones, ability to feed, and respiratory complications, such as aspiration because of poor cry and poor cough. In older children, medical history focuses on cognitive abilities, motor abilities, muscle weakness, disease progression, joint contractures, scoliosis and spinal deformities, nutritional status, signs of respiratory compromise, hospitalizations, and infections.
Information in the medical history that may help identify the specific CMD subtype:. Congenital head lag as a result of marked cervicoaxial hypotonia associated with progressive cervical stiffness: SELENON-related CMD Family history. Most of the muscular dystrophies described to date are inherited in an manner. In the non-, small nuclear families typical of the US and Europe, often only one individual in a family with an autosomal recessive disorder is. In contrast, most individuals with collagen VI-deficient CMD and all reported individuals with L-CMD have a and therefore represent cases (i.e., a single occurrence in a family). Documentation of relevant findings in family members with weakness can be accomplished through review of medical records. It is appropriate to review the medical records and any available tissue samples of sibs of the who have died in the newborn period.
Physical examination. Findings that may help with identification of the specific CMD subtype:. Intellectual disability associated with marked behavioral disturbances: suggestive of MEB disease, especially those with POMGNT1 pathogenic variants Eye examination by a pediatric ophthalmologist.
Eye examinations are recommended in the presence of signs or symptoms of ocular involvement or if dystroglycanopathy is suspected. Serum CK concentration. In general CMD subtypes with no abnormality in merosin expression (collagen VI-deficient CMD, SELENON-related CMD, L-CMD) show normal or mildly increased serum concentration of CK, while those with primary merosin deficiency (laminin alpha-2 deficiency) or secondary merosin deficiency (dystroglycanopathies) have high serum concentration of CK (4x normal values). (See.) Neuroimaging. MRI can be used to guide diagnosis.
The two CMD subtypes with brain abnormalities visualized on MRI are laminin alpha-2 deficiency and the dystroglycanopathies. In the dystroglycanopathies, structural changes (including hydrocephalus, brain stem hypoplasia, cerebellar cysts) or abnormalities in neuronal migration (lissencephaly or polymicrogyria) are common. White matter changes may regress with time. Muscle imaging. Distinct recognizable patterns on muscle MRI in persons with spinal rigidity, normal merosin staining of skin or muscle biopsy, and normal serum CK concentrations can help distinguish between collagen VI-deficient CMD, SELENON-related CMD, and L-CMD and between the CMDs and the overlapping phenotypes considered in the differential diagnosis that are caused by pathogenic variants in RYR1, GAA (encoding acid maltase) or DNM2 (see ). Molecular genetic testing. With the expanding role of in confirming the diagnosis of a CMD subtype, the trend recently has been to perform molecular genetic testing without muscle biopsy when the medical history, physical examination, and neurologic examination support the diagnosis of a CMD.
For example, in the past the evaluation of an infant with head lag, hypotonia, and brain white matter abnormalities on MRI who is suspected of having laminin alpha-2 deficiency may have been to perform a skin biopsy first to demonstrate merosin deficiency followed by LAMA2 molecular genetic testing. However, currently the evaluation may proceed directly to molecular genetic testing (without skin biopsy) depending on the level of suspicion, the exclusion of other more common diagnoses, and the confidence of the neurologist in the diagnosis. In contrast, when multiple genes may need to be tested, as in the confirmation of the diagnosis of a dystroglycanopathy, performing immunohistochemical analysis of a muscle biopsy may identify the subtype prior to proceeding with.
To establish/confirm the diagnosis of a CMD subtype in a using. For an introduction to multigene panels click. More detailed information for clinicians ordering genetic tests can be found. Once the pathogenic variants in an disorder or the in an disorder is identified, of the parents is needed to clarify and to provide accurate information to family members. It is always necessary to determine if the has two autosomal recessive variants (one inherited from each parent) or if the proband has a autosomal dominant variant that is not present in either parent (if they are not ). Muscle histology typically shows a dystrophic or myopathic nonspecific pattern that does not suggest a myopathy, mitochondrial disorder, or denervating disorder. The most significant dystrophic features are fiber size variability, presence of increased endomysial fibrosis, and variably necrotic and/or regenerative fibers.
In some individuals with CMD, muscle biopsy may only show fiber size variation with absence of or only mild manifestations of fibrosis, necrosis, or regeneration. A muscle biopsy may be indicated if the diagnosis based on clinical examination remains unclear or does not confirm a diagnosis. Immunohistochemical staining of muscle and/or skin can in some instances confirm protein deficiencies that can establish or exclude the diagnosis of a CMD subtype or help guide confirmatory. Immunostaining of muscle can detect deficiencies of the proteins laminin alpha-2 (merosin), collagen VI, and alpha dystroglycan ; immunostaining of skin can detect deficiencies of laminin alpha-2 and collagen VI. Immunostaining is not diagnostic or specific in SELENON-related CMD or L-CMD. When testing for presence of large proteins in muscle (e.g., laminin alpha-2) it may be necessary to use more than one antibody in order to detect partial deficiencies. Partial merosin deficiency may be primary (i.e., caused by mutation of LAMA2, encoding laminin alpha-2) or secondary (i.e., caused by mutation of one of the genes associated with the dystroglycanopathies).
Congenital myopathies (including, centronuclear myopathy, and ) typically have normal or near-normal serum CK concentration and histologic evidence on muscle biopsy of developmental/structural muscle changes rather than dystrophic changes. The prognosis depends on the severity of presentation, which can range from fetal akinesia or floppy infant syndrome requiring mechanical ventilation to later-onset milder symptoms. Affected individuals do not develop significant joint contractures and the motor impairment is stable or may even slowly improve, although spinal deformities and respiratory complications may be severe or progressive. Severe facial or oculomotor weakness seen in certain congenital myopathies is not found in the early stages of CMD, but may occur in the late stages of the subtypes laminin alpha-2 deficiency and the dystroglycanopathies. Congenital myopathy caused by mutation of RYR1 can be a phenotypic mimic of several conditions, including SELENON ( SEPN1)-related CMD with a clinical picture of multiminicore myopathy or a CMD-like presentation, with early onset hypotonia, axial weakness, and respiratory insufficiency. Limb-girdle muscular dystrophy (LGMD).
The disease spectrum within the dystroglycanopathies ranges from onset with CNS and eye involvement, to congenital onset without eye involvement and mild development delay, to a later-onset muscle weakness or limb-girdle muscular dystrophy (LGMD) with or without intellectual disability. Pathogenic variants in any of the six dystroglycanopathy-associated genes can result in CMD or LGMD. Similarly, the collagen VI-deficient myopathies range from Ullrich CMD to Bethlem myopathy, which is considered a LGMD.
(glycogen storage disease type II, GSD2, acid maltase deficiency) in the infantile form presents within the first months of life with hypotonia, head lag, and marked cardiomegaly. Respiratory insufficiency in the first year can lead to frequent pulmonary infections. Additional features include moderate hepatomegaly and macroglossia. Diagnosis is confirmed through identification of pathogenic variants in GAA, the encoding alpha-glucosidase (GAA), or by measuring deficient serum GAA enzyme (also called acid maltase) activity. (FSHD) is characterized by facial diplegia, congenital deafness, intellectual disability, and seizures. Most children become wheelchair users in childhood.
Facial weakness is the earliest and most prominent sign, distinguishing FSHD from CMD: the infant is unable to smile and has little or no facial expression. Infantile FSHD may be inherited as a or in fashion. FSHD is diagnosed by a molecular genetic test that identifies of integral copies of a 3.3-kb DNA repeat motif, D4Z4, which is located in the subtelomeric region of 4q35. (MSS) presents with cerebellar ataxia with cerebellar atrophy, early-onset cataracts, mild to severe intellectual disability, hypotonia, and muscle weakness. Initial hypotonia is followed by evidence of cerebellar involvement with truncal ataxia, dysdiadochokinesia, and dysarthria. Serum CK is two to four times normal.
Diagnosis is confirmed by clinical picture, brain MRI cerebellar findings, electron microscopic changes (autophagic vacuoles, membranous whorls, and electron-dense double membrane structures associated with nuclei) on muscle biopsy, and of SIL1, the only known to be associated with MSS. Inheritance is. (CMS) are a group of diseases with pathogenic variants in genes that are implicated in the neuromuscular junction leading to weakness and fatigability and often respiratory and feeding complications. Arthrogryposis; club feet resulting from fetal immobility; bulbar, oculomotor, or facial involvement; diurnal variability of performance; and unexpected rapid failure in motor, respiratory, and/or feeding functions are typical clinical findings but are not always present.
Electrophysiologic studies specific for the neuromuscular junction (EMG with repetitive stimulation, stimulated single fiber) may identify abnormal neuromuscular transmission but are often difficult and require expertise. Included in the differential diagnosis of early-onset muscle disease associated with rigid spine are the following disorders:.
Prevalence of CMD The incidence and prevalence of CMD in populations are not well documented because of limited molecular genetic confirmation of the diagnosis and use of different diagnostic classification systems in the past. The incidence of all forms of muscular dystrophies has been estimated at 1:21,500 with a prevalence of 1:125,000 in northeastern Italy and an incidence of 1:16,000 in western Sweden. The point prevalence (i.e., the total number of cases of a specific disease in existence in a given population at a specific point in time) ranges from 0.68 to 2.5 per 100,000. The failure to diagnosis primary muscle disease in individuals with mild muscle weakness with and without intellectual disability may continue to result in underestimation of the prevalence of CMD ,. In addition, the relative frequency of CMD subtypes varies in different populations.
For example, in Japan the most commonly diagnosed CMD subtype is Fukuyama CMD caused by a in FKTN (the encoding fukutin), followed by collagen VI-deficient CMD. In contrast, FKTN pathogenic variants are rare in other populations. Laminin alpha-2 deficiency and collagen VI-deficient CMDs are the most common subtypes in many countries with populations of European origin. Genetic Counseling Genetic counseling is the process of providing individuals and families with information on the nature, inheritance, and implications of genetic disorders to help them make informed medical and personal decisions. The following section deals with genetic risk assessment and the use of family history and genetic testing to clarify genetic status for family members. This section is not meant to address all personal, cultural, or ethical issues that individuals may face or to substitute for consultation with a genetics professional. My passport backup. Risk to Family Members —Autosomal Dominant CMD Sibs of a.
The risk to the sibs of the proband depends on the genetic status of the proband's parents: if the found in the proband cannot be detected in the leukocyte DNA of either parent, the risk to sibs is low but greater than that of the general population because of the possibility of, and thus in subsequent pregnancies is offered. Offspring of a.
Each child of an individual with a dominantly inherited CMD has a 50% chance of inheriting the. Related Genetic Counseling Issues Family planning. The optimal time for determination of genetic risk, clarification of status, and discussion of the availability of prenatal testing is before pregnancy. Muscle biopsy banking. Future research and diagnostic studies may be performed on muscle tissue that has been flash frozen.
Banking tissue or storing leftover samples from a diagnostic biopsy may be worthwhile for future studies. DNA banking is the storage of DNA (typically extracted from white blood cells) for possible future use.
Because it is likely that testing methodology and our understanding of genes, allelic variants, and diseases will improve in the future, consideration should be given to banking DNA of individuals. A CMD BioBank, part of the NIGMS repository at Coriell Medical Institute, offers DNA banking as well as banking or cell lines. Prenatal Testing and Preimplantation Genetic Diagnosis Molecular genetic testing. Once the (s) have been identified in an family member, prenatal testing for a pregnancy at increased risk and for CMD are possible.
Biochemical testing. Prenatal testing for pregnancies at 25% risk for laminin alpha-2 deficiency is possible provided that immunostaining has documented complete merosin deficiency in the muscle of an sib who has typical clinical findings. This method may be most useful when only one LAMA2 has been identified on.
Immunostaining must be done on flash-frozen chorionic villi (obtained at 10-12 weeks’ gestation). In 70 prenatal cases, concordance between immunostaining of chorionic villi and linkage analysis for the LAMA2 was 100%, suggesting that immunostaining on CVS is both accurate and sensitive. Note: Gestational age is expressed as menstrual weeks calculated either from the first day of the last normal menstrual period or by ultrasound measurements. The CMDIR is a patient self-report registry with the goal to register the global muscle disease population including persons with congenital myopathy, congenital muscular dystrophy, and congenital myasthenic syndrome.
The CMDIR registers individuals of all ages with symptoms from birth through late onset (limb-girdle). Registrants will receive educational information and connections to others in the CMD community, and will be contacted about potential participation in clinical trials for their CMD subtype. Polysomnography to identify individuals with nocturnal hypoventilation, to evaluate individuals with symptoms of hypercapnea (daytime headache, restless sleep, loss of concentration), and to evaluate individuals with reduced forced vital capacity, particularly those with CMD subtypes associated with a rigid spine, axial weakness, and/or signs of diaphragmatic weakness (detected by a drop in FVC from sitting to supine).
Additional indications for polysomnography include testing in the very young or those with developmental delay in whom reliable, consistent pulmonary function testing can be difficult to obtain. Treatment of Manifestations No definitive treatments exist for the muscular dystrophies; however, multidisciplinary medical care improves quality of life and longevity. Management should be tailored to each individual, their specific CMD subtype, and rate of progression. Respiratory therapy and use of respiratory aids including assisted cough and hyperinsufflation devices, Percussionaire ®, noninvasive ventilatory support, or mechanical ventilation via tracheostomy are appropriate for those with respiratory insufficiency. Physical therapy and stretching exercises help promote mobility and prevent contractures. Mechanical assistive devices including canes, walkers, orthotics, and wheelchairs can be used as needed to help ambulation and mobility. Posture in vertical, sitting, and supine positions has to be evaluated and assisted if necessary as improved posture may positively affect chest expansion.
Surgical intervention may be needed for orthopedic complications such as foot deformity, joint contractures, and scoliosis. Pros and cons of surgery for hip dislocation or joint contractures need to be considered given that any functional benefit may be insignificant compared to the high risk of pain and rapid relapse. Proactive trunk bracing (plexidur Garchois brace) is used in some countries to reduce the degree of deformity and to slow the progression of scoliosis in order to delay consideration of surgical intervention until puberty. Speech therapy may be indicated.
Close attention to oral hygiene is indicated. Assistance in education (school technical aide) and social and emotional support and stimulation can improve the sense of social involvement and productivity and can reduce the sense of social isolation common in those with CMD. Steroid treatment using dosages based upon guidelines used in the treatment of has been reported in the dystroglycanopathies. In those who respond, the use of steroids appears to support prolonged ambulation.
Mercuri E, Messina S, Bruno C, Mora M, Pegoraro E, Comi GP, D'Amico A, Aiello C, Biancheri R, Berardinelli A, Boffi P, Cassandrini D, Laverda A, Moggio M, Morandi L, Moroni I, Pane M, Pezzani R, Pichiecchio A, Pini A, Minetti C, Mongini T, Mottarelli E, Ricci E, Ruggieri A, Saredi S, Scuderi C, Tessa A, Toscano A, Tortorella G, Trevisan CP, Uggetti C, Vasco G, Santorelli FM, Bertini E. Congenital muscular dystrophies with defective glycosylation of dystroglycan: a population study. 2009; 72:1802–9.
© 1993-2018, University of Washington, Seattle. GeneReviews is a registered trademark of the University of Washington, Seattle. All rights reserved. GeneReviews® chapters are owned by the University of Washington. Permission is hereby granted to reproduce, distribute, and translate copies of content materials for noncommercial research purposes only, provided that (i) credit for source and copyright (© 1993-2018 University of Washington) are included with each copy; (ii) a link to the original material is provided whenever the material is published elsewhere on the Web; and (iii) reproducers, distributors, and/or translators comply with the. No further modifications are allowed.
For clarity, excerpts of GeneReviews chapters for use in lab reports and clinic notes are a permitted use. For more information, see the. For questions regarding permissions or whether a specified use is allowed, contact:.
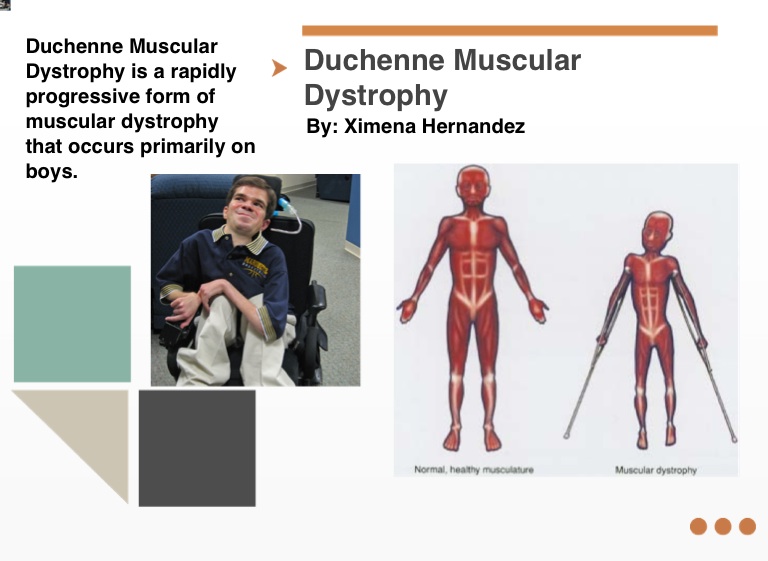
Muscular dystrophy is a group of genetic diseases that cause progressive weakness of the body's muscles. Some types of muscular dystrophy will present symptoms in early childhood, while other types will appear in adulthood. Different muscle groups also may be affected depending on the type of muscular dystrophy. Duchenne muscular dystrophy is the most common form of childhood muscular dystrophy.
It generally appears in 3-to 6-year-old boys and worsens rapidly. Becker muscular dystrophy has symptoms similar to Duchenne muscular dystrophy. However, symptoms most commonly begin in the teens to mid-20s and progress slowly.
Different types of muscular dystrophy begin to show symptoms at different ages and, depending on the type of muscular dystrophy, different muscle groups throughout the body will be affected. To diagnose any form of muscular dystrophy, a physician will take a thorough medical history and perform a physical examination. Some diagnostic tests also may be ordered. A blood test will show if the enzyme creatine kinase is leaking from the muscle cells, causing abnormally high levels in the blood. While high blood levels of creatine kinase don’t necessarily confirm that a patient has muscular dystrophy, it is an indication of muscle disease. Measure electrical activity of muscle and nerve function to detect the presence, location and extent of diseases that can damage muscle tissue.
A muscle biopsy - in which a small piece of the muscle is removed for examination under a microscope - is usually taken in order to confirm the condition. Under the microscope, the muscle of a positive biopsy generally shows dead tissue and abnormally large muscle fibers.
Muscular Dystrophy On Flowvella Review
In the late stages of muscular dystrophy, fat and other tissues replace the dead muscle tissue. Genetic testing can be performed to determine the gene mutations that caused muscular dystrophy. Currently, there is no known cure for any of the muscular dystrophies. And exercise help prevent muscles from contracting permanently around joints and avoid curvature of the spine. Sometimes surgery is needed to release tight, painful muscles. Breathing exercises can help delay weakening of the respiratory muscles.
Muscular Dystrophy On Flowvella App
Some symptoms can be treated, and progression may be slowed with medications. Prednisone, a powerful corticosteroid drug, is currently used to temporarily relieve muscle weakness and slow muscle damage, as well as help with respiratory function. For some types of muscular dystrophy, heart problems may arise that can be treated with medication or a. Researchers are looking into gene therapy that would enable muscles to produce dystrophin (for Duchenne and Becker muscular dystrophies), as well as other therapies to find a cure for all the muscular dystrophies.